


For the past decade, hypoglossal nerve stimulation (HNS) has quietly become one of the most important non-CPAP therapies for obstructive sleep apnea (OSA). For the right patient, it works—and sometimes works remarkably well.
But it has always come with a catch: invasiveness, cost, and variability.
A recent study published in CHEST—“Effect of Novel Hypoglossal Stimulation on Airflow and Airway Collapsibility in OSA”—offers a glimpse at what the next iteration of HNS might look like.
And if these findings translate to real-world sleep practice?
We may be looking at a change to therapy.
What This Study Actually Did (And Why It’s Different)
Instead of surgically implanting a cuff electrode, the investigators used:
Ultrasound guidance
Percutaneous insertion (through the skin)
A multi-contact linear electrode array
Targeting the distal hypoglossal nerve branches
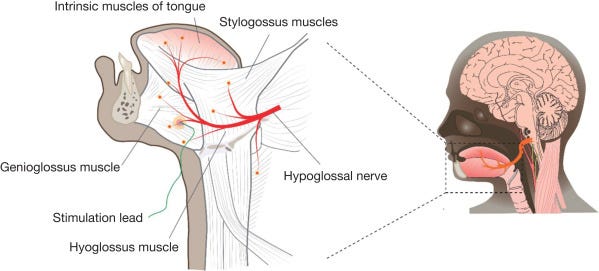
Rather than committing to a fixed electrode position, they could:
Adjust location in real time
Test multiple stimulation patterns
Identify the optimal configuration for each patient
The Headline Result: CPAP-Level Airflow Improvements…Without CPAP
During drug-induced sleep endoscopy (DISE), the team induced airway collapse by dropping CPAP and monitoring .
Then they turned on stimulation.
Airflow went from near-zero to levels equivalent to therapeutic CPAP. Active Pcrit improved by ~7 cm H₂O
That magnitude is not trivial.
For context:
Oral appliances, surgery, and positional therapy typically shift Pcrit by ~2–6 cm H₂O
Moving Pcrit below –5 cm H₂O often resolves OSA physiology
Why This Could Be a Big Deal: Three Shifts
1. From Surgery → Procedure → Potentially Office-Based
Current HNS:
OR surgery, 2 hours
Multiple incisions
Weeks of recovery/titration
This approach:
Percutaneous
< 30 minutes in study setting
Theoretically adaptable to clinic-based placement
It’s not hard to imagine a future where HNS becomes:
“An interventional sleep procedure” rather than an implant surgery
2. From Fixed Hardware → Personalized Neurostimulation
The ability to:
Map the nerve
Test multiple electrode pairs
Optimize amplitude in real time
…opens the door to precision neuromodulation.
This is the same evolution we’ve seen in other specialties:
Cardiac electrophysiology
Deep brain stimulation
Pain neuromodulation
OSA may be next.
3. From Strict Selection → Expanded Eligibility
Because of the invasiveness/implant nature, today’s HNS criteria exclude many patients:
BMI limits
Concentric collapse
Uncertain response rates
But imagine a workflow where:
A percutaneous probe is placed during DISE
Airflow response is tested in real time
Only responders move forward to longer-term therapy
That’s a physiology-driven selection model, not a population-based guess. And perhaps that opens the therapy to more OSA patients/snorers.
Where This Still Falls Short
Before we get ahead of ourselves:
Small sample size (n=14)
Acute physiology—not overnight sleep
Conducted under propofol sedation (artificial sleep)
No full implantation yet
Exciting, but still a ways to go.
The Bigger Picture: HNS Is Evolving
This paper isn’t just about a new technique. It’s another incremental evolution in the treatment of OSA.
From:
Static anatomy
One-size-fits-all devices
To:
Dynamic physiology
Targeted, adaptable interventions
If CPAP was the first era…
And implantable HNS the second…
This might represent the beginning of HNS 3.0 (with 2.0 belonging to Nyxoah/LivaNova following Inspire’s 1.0).
Novel nerve targets
Less invasive
More improvement
Potentially more scalable
We’re not there yet.
But this is one of the more compelling glimpses of what that future might look like. We look forward to sharing more exciting research in this field.
Best, Robson & Chris